Thursday, July 17, 2014

Care Not Killing Alliance: Falconer bill is a recipe for the abuse of elderly and disabled people

This article was originally published by Peter Saunders on his blog.

On the eve of the House of Lords’ debate on Lord Falconer's Assisted Dying Bill, Care Not Killing, an alliance of 40 organisations, has called on peers to reject the proposed legislation on grounds of public safety.

Campaign Director Dr Peter Saunders said, 

‘This bill is a recipe for the abuse of elderly and disabled people. The pressure vulnerable people will feel to end their lives if assisted suicide is legalised will be greatly accentuated at this time of economic recession with families and health budgets under pressure. It will quite simply steer them toward suicide.’ 
‘Any change in the law to allow assisted suicide or euthanasia would place pressure on vulnerable people to end their lives for fear of being a financial, emotional or care burden upon others. This would especially affect people who are disabled, elderly, sick or depressed.' 
‘In Washington, where assisted suicide is legal under a law very similar to that proposed by Falconer, 61% of people opting for assisted suicide give the fear of being a burden to family, relatives and caregivers as a key reason.’

The 85 assisted suicide deaths in 2012 in Oregon would equate with a similar law to 1,232 in England and Wales (14 times that of Oregon) and the Oregon experience raises many other causes for concern:
  1. There has been a steady increase in annual numbers of people undergoing assisted suicide in Oregon.
  2. The Oregon health department is funding assisted suicide but not treatment for some cancer patients.
  3. Patients are living for many years after having been prescribed lethal drugs for ‘terminal illness’ showing that the eligibility criteria are being stretched.
  4. The vast majority of those choosing to kill themselves are doing so for existential reasons rather than on the basis of real medical symptoms.
  5. Fewer than three per cent of patients are being referred for formal psychiatric or psychological evaluation.
  6. More than ten per cent of patients dying under the Act do not have terminal illnesses.
  7. Some doctors know the patient for less than a week before prescribing the lethal drugs.
  8. The fact that almost a third of patients dying under the Act report inadequate pain control or concerns about pain shows that palliative care provision in Oregon is unsatisfactory.
  9. The presence of no independent witnesses in over 80% of cases is a recipe for elder abuse.
  10. According to research 25% of cases of assisted suicide in Oregon involve people who are clinically depressed

Elder abuse and neglect by families, carers and institutions are real and dangerous and this is why strong laws are necessary. Action on Elder Abuse, for example, states that more than 500,000 elderly people are abused every year in the United Kingdom. Sadly, the majority of such abuse and neglect is perpetrated by friends and relatives, very often with financial gain as the main motive. It would be very naive to think that many of the elderly people who are abused and neglected each year, as well as many severely disabled individuals, would not be put under pressure to end their lives if assisted suicide were permitted by law.

Dr Nitschke has 48 hours to defend being struck off by medical board.

This article was originally published on July 17 by Paul Russell on the HOPE Australia blog.

B
Paul Russell
y Paul Russell, the Director of HOPE Australia (Preventing euthanasia and assisted suicide) and the Vice Chair of the Euthanasia Prevention Coalition - International.


The head of Exit International, Dr Philip Nitschke held a press conference ahead of an Exit meeting in Melbourne Australia today.

The Age Newspaper is reporting that Dr Nitschke claims that he has 48 hours to mount a defence against the medical board of Australia, AHPRA, whom the report says, wants Nitschke deregistered as a medical practitioner.

The Australian Health Practitioner Regulation Agency (AHPRA), now has a media statement on their website confirming this move, saying:

Immediate action is a serious step. The threshold for the Board to take immediate action is high and is defined in section 156 of the National Law. To take immediate action, the Board must reasonably believe that: 
because of their conduct, performance or health, the practitioner poses a ‘serious risk to persons’ and that it is necessary to take immediate action to protect public health or safety, 
or that the practitioner’s registration was improperly obtained, 
or the practitioner or student’s registration was cancelled or suspended in another jurisdiction.
Read the full press statement HERE:

The ABC News is confirming: Speaking in Melbourne, Dr Nitschke said 
"the Medical Board, under pressure, has suddenly decided that immediate deregistration seems to be the best option. So that's what they decided to do."
This detail comes on the back of an ABC 7:30 Report recently where it was disclosed that Dr Nitschke spoke and corresponded with a Perth WA man who admitted in an email to Exit that he intended to suicide. Suicide Prevention authorites were outraged that Dr Nitschke admitted on television that he did nothing to try and stop the man.

In what is seen by this writer as a very low blow, Nitschke is claiming that the man in question, Nigel Brayley, was a serial killer. As if that is some justification for not acting and for welcoming his death. It is known that Brayley did have an association with the death of two people - one his wife - but no charges had been laid against him and it remains unclear whether he was ever considered a suspect.

Care Minister (UK) promotes assisted suicide as treatment option for people with disabilities and the elderly.


Dr Peter Saunders
By Peter Saunders - Campaign Director, Care Not Killing Alliance.

There is really something quite chilling about seeing the Care Minister backing assisted suicide as a treatment option for disabled and elderly people.

But that is exactly what Liberal Democrat Minister Norman Lamb, the cabinet member responsible for providing care for dementia and other serious disabilities, has done today.

It is bitterly ironic that he has spoken out on the very day that the CEOs of four major charities representing elderly and disabled people have written to members of the House of Lords warning about the dangers of passing Lord Falconer’s Assisted Dying Bill and one day before disabled people’s representatives take to the streets of Westminster and the airwaves of the nation to protest.

Falconer's bill is no less than a recipe for the abuse of elderly and disabled people.

In Washington, where assisted suicide is legal under a law very similar to that proposed by Falconer, 61% of people opting for assisted suicide give the fear of being a burden to family, relatives and caregivers as a key reason.


The pressure people will feel to end their lives if assisted suicide or euthanasia is legalised will be greatly accentuated at this time of economic recession with families and health budgets under pressure. It will quite simply steer them toward suicide.

Elder abuse and neglect by families, carers and institutions are real and dangerous and this is why strong laws are necessary.

Any change in the law to allow assisted suicide or euthanasia would place pressure on vulnerable people to end their lives for fear of being a financial, emotional or care burden upon others. This would especially affect people who are disabled, elderly, sick or depressed.

Parliament has rightly rejected the legalisation of assisted suicide and euthanasia in Britain three times since 2006 out of concern for public safety - in the House of Lords (2006 and 2009) and in Scotland (2010) - and repeated extensive enquiries have concluded that a change in the law is not necessary.

Wednesday, July 16, 2014

Dutch ethicist - “Assisted Suicide: Don’t Go There”

This is the original article that was written for the Daily Mail by Professor Theo Boer.
The Daily Mail published this article instead. 
Boer gave EPC permission to publish his original article.

Professor Theo Boer
Professor Theo Boer
Authorized version, July 16, 2014.


In 2001 The Netherlands was the first country in the world to legalize euthanasia and, along with it, assisted suicide. Various safeguards were put in place to show who should qualify and doctors acting in accordance with these safeguards would not be prosecuted. Because each case is unique, five regional review committees were installed to assess every case and to decide whether it complied with the law. For five years after the law became effective, such physician-induced deaths remained level - and even fell in some years. In 2007 I wrote that ‘there doesn’t need to be a slippery slope when it comes to euthanasia. A good euthanasia law, in combination with the euthanasia review procedure, provides the warrants for a stable and relatively low number of euthanasia.’ Most of my colleagues drew the same conclusion.

But we were wrong - terribly wrong, in fact.


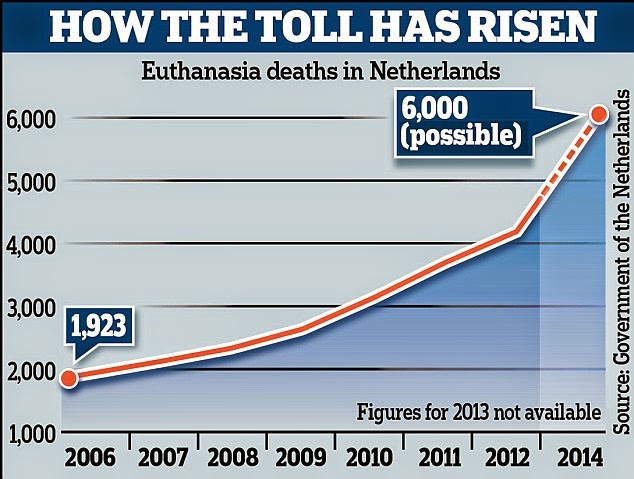
In hindsight, the stabilization in the numbers was just a temporary pause. Beginning in 2008, the numbers of these deaths show an increase of 15% annually, year after year. The annual report of the committees for 2012 recorded 4,188 cases in 2012 (compared with 1,882 in 2002). 2013 saw a continuation of this trend and I expect the 6,000 line to be crossed this year or the next. Euthanasia is on the way to become a ‘default’ mode of dying for cancer patients.

Alongside this escalation other developments have taken place. Under the name ‘End of Life Clinic,’ the Dutch Right to Die Society NVVE founded a network of travelling euthanizing doctors. Whereas the law presupposes (but does not require) an established doctor-patient relationship, in which death might be the end of a period of treatment and interaction, doctors of the End of Life Clinic have only two options: administer life-ending drugs or sending the patient away. On average, these physicians see a patient three times before administering drugs to end their life. Hundreds of cases were conducted by the End of Life Clinic. The NVVE shows no signs of being satisfied even with these developments. They will not rest until a lethal pill is made available to anyone over 70 years who wishes to die. Some slopes truly are slippery.

Other developments include a shift in the type of patients who receive these treatments. Whereas in the first years after 2002 hardly any patients with psychiatric illnesses or dementia appear in reports, these numbers are now sharply on the rise. Cases have been reported in which a large part of the suffering of those given euthanasia or assisted suicide consisted in being aged, lonely or bereaved. Some of these patients could have lived for years or decades.


Whereas the law sees assisted suicide and euthanasia as an exception, public opinion is shifting towards considering them rights, with corresponding duties on doctors to act. A law that is now in the making obliges doctors who refuse to administer euthanasia to refer their patients to a ‘willing’ colleague. Pressure on doctors to conform to patients’ (or in some cases relatives’) wishes can be intense. Pressure from relatives, in combination with a patient’s concern for the wellbeing of his beloved, is in some cases an important factor behind a euthanasia request. Not even the Review Committees, despite hard and conscientious work, have been able to halt these developments.


I used to be a supporter of legislation. But now, with twelve years of experience, I take a different view.

At the very least, wait for an honest and intellectually satisfying analysis of the reasons behind the explosive increase in the numbers. Is it because the law should have had better safeguards? Or is it because the mere existence of such a law is an invitation to see assisted suicide and euthanasia as a normality instead of a last resort? Before those questions are answered, don’t go there. Once the genie is out of the bottle, it is not likely to ever go back in again.

Theo Boer is a professor of ethics at the Protestant Theological University at Groningen. For nine years he has been a Member of a euthanasia Regional Review Committee. The Dutch Government has five such committees that assess whether a euthanasia case was conducted in accordance with the law. The views expressed here represent his views as a professional ethicist, and not of any institution.

Links to important articles:

Euthanasia Lobby assembles tiny group of doctors to create false impression of medical support for assisted suicide bill

By Dr Peter Saunders - The Campaign Director of the Care Not Killing Alliance in the UK.
This article was originally published by Peter Saunders on his blog.

Peter Saunders
According to the Guardian, ‘twenty-seven leading (medical) figures’ have written to peers asking them to back Falconer’s Bill.

The Guardian gives only a few isolated quotes from their letter and names only five of the signatories.

Of these five, three (Michael Rawlins, Graham Winyard and Terence English) are well-known members of Health Professionals for Assisted Dying (HPAD), the medical wing of the Voluntary Euthanasia Society, now rebranded Dignity in Dying.

They are listed on its supporters’ page amongst HPAD’s 602 health professional members. Even if we assumed that all of these 600 or so were registered medical practitioners (and many are actually either retired doctors or non-medics) they would still make up only a tiny minority of the UK’s 260,000 registered GPs and specialists – to be precise less than a quarter of one per cent.

I expect that we would find most of the unnamed signatories on the HPAD list as well – which may well be why the Guardian has opted not to tell us their names.

The two named signatories who don’t appear on the HPAD list are John Ashton, a well-known backer of assisted suicide, and Sir Richard Thompson, the president of the Royal College of Physicians.

However, as the Guardian acknowledges, this means very little as The Royal College of Physicians (RCP) and Royal College of GPs (RCGP) are both opposed to assisted dying. In their most recent surveys of their members' views, 73.2% of hospital doctors and 77% of family doctors said they were against legalising it.

The Guardian does not tell us, however, that included amongst other official UK doctors’ bodies opposing any change in the law are the British Medical Association (BMA), the Association for Palliative Medicine (APM) and the British Geriatric Society (BGS).

Dr Mark Porter
As Mark Porter , chairman of the BMA council, said earlier this year, ‘The BMA remains firmly opposed to legalising assisted dying. This issue has been regularly debated at the BMA's policy forming annual conference and recent calls for a change in the law have persistently been rejected.’

The British Geriatric Society in 2010 issued a strong statement on assisted suicide which outlined its concerns about how a change to the law would remove protection from vulnerable elderly people. The full statement is most worthy of study by all who take an interest in this debate.

The World Medical Association (WMA) has also recently reiterated its strong opposition to euthanasia. The WMA similarly opposes assisted suicide.

Disability leader, Simon Stevens: Why I oppose assisted suicide.

This article was written by Simon Stevens, an independent disability issues consultant and published by the Huffington Post under the title: Give Me The Right to Live , Not Die.

By Simon Stevens, Huffington Post, July 15, 2014

I am one if many disabled people that has been vocal in their opposition to this dangerous legislation, that is likely to be the starting point to the normalisation of 'mercy killings' and a societal pressure upon sick and disabled people to 'do the right' thing. 

The supporters of the bill, all of them who are not disabled or terminally ill, backed by 'Dignity in Dying', who were previously called the Voluntary Euthanasia Society, wish to present a nice clean bill. The killing will be restricted to those who are terminally ill, with less than 6 months, or 183 days, to live, as agreed by two doctors, and have the mental capacity to consent to killing themselves, which the supporters want to make clear is 'kind' assisted dying, not the less publicly accepted assisted suicide, a difference in words that make little difference to its results, premature death. The supporters want to make us believe the bill has nothing to do with disabled people, and that 'we' are in some way immoral for trying to interfere in things that are not our business.


The problem with this clean picture is that it ignores what is in fact a very unclear picture. Firstly, it is extremely hard to separate impairment from terminal illness as they are often interlinked, and in the public's eye, it is all 'needless suffering'. Secondly, no doctor on the planet would be prepared to diagnose anyone in having exactly 183 days left to live since no illness is predictable and someone's journey will be affected by so many factors, including their own attitudes towards their state of being. While some illnesses show their symptoms at this supposedly six month point, others may not.

The key point the supporters are using to win their case is ending 'needless suffering', citing pain and indignity as reasons to die. Suffering, pain and especially indignity is very much in the eye of the beholder and can not be measured. I find the term indignity offensive because it is often used by those who are not disabled or ill to describe how they think they will feel if it happened to them, based on their deep rooted prejudices towards impairment and sickness. You hear people say they rather die than end up having to use incontinence pads or nappies, so what the hell does it say about their opinion of the millions of people around the world perfectly happy wearing them? I wear nappies myself and I talk about 'nappy pride', something I am certainly not alone in. Suffering is a part of what makes us human, and stronger people, and no one has a right to escape it.

And if people want to end 'needless suffering', why just offer a painless suicide to those experiencing 'health suffering'? Why not economic suffering like people in debt or who have lost their job? Why not victims of crime or those who are confused about their sexuality or gender? Why does the bill discriminate those suffering and lack mental capacity, or who are experiencing long term chronic pain who do not have a terminal illness? I am sure if this bill is passed, a second bill will quickly follow to redress these anomalies, bringing the future many disabled people are fearing.

The supporters try to justify the bill by talking about people's 'right' to have 'choice and control' over their death. But many disabled people do not have choice and control over how they live, and yet despite many years of campaigning, it does not receive anywhere near the support or media attention this supposed right has. It is also impossible for anyone to have a free choice without taking into account their environment and the external pressures placed upon them by families and society. If people are not receiving the proper level of health and social care they are entitled to, this is certainly going to have an impact on their decision, which would never be taken at face value if they were not disabled.

I have felt suicidal a few times in my life, each time because I was unhappy with the current situation from my environment, having little to do with my impairments, but each time I was able to resolve the problems causing my unhappiness, bouncing back stronger than ever, making further and amazing contributions to others when I had assumed I completed my time here. Suicide is a long term solution to a short term problem, and people who want to die need proper and appropriate emotional support, whatever their situation, not a prescription of life-removing drugs.


Friday is a test to see how serious the country is in relation to the full inclusion of disabled people as equal citizens, and I hope it passes it by saying no to the bill.

Monday, July 14, 2014

Desmond Tutu confuses assisted dying with switching off life support.

This article was written by Renee Joubert, and published by Euthanasia Free New Zealand.


The “Falconer Assisted Dying Bill” will receive it’s second reading in the UK House of Lords on Thursday. It proposes legalising physician-assisted suicide for the terminally ill who has been given 6 months or less to live.

Bishop Desmond Tutu has allegedly voiced his support for “assisted dying”, with reference to the terminal illness of his friend Nelson Mandela, former president of South Africa, during 2013.

According to CNN (27 June 2013) and News 24 (4 July 2013), the 94-year-old Nelson Mandela was in a persistent vegetative state and on life support to help him breathe. Medical staff advised his family that the machines should be switched off. Mandela eventually died on 5 December 2013. It seems that the delay could have been caused, at least in part, by a family dispute.

Some subsequent news reports published elsewhere, such as this one by 3News, claimed only that Mandela had been suffering from a recurring lung infection and that he had been “receiving intensive care at home” since 1 September.

Interesting that Bishop Desmond Tutu now admits publicly that Mandela was indeed on life support and that “prolonging his life was an affront to his dignity”, according to an article on BBC.com.

“I think when you need machines to help you breathe, then you have to ask questions about the quality of life being experienced and about the way money is being spent.”

Belgium's Dr Death offers tour of Auschwitz.

By Alex Schadenberg
Auschwitz
International Chair - Euthanasia Prevention Coalition

An article in the Daily Mail (UK) reported on a disturbing decision by euthanasia activist, Dr Wim Distelmans who is offering a tour of the Nazi death camp, Auschwitz, a tour that he calls "inspiring." Distelmans is charging around 600 euro for a tour of the gas chambers and a seminar on the issues surrounding euthanasia.

Distelmans, who operates a euthanasia clinic in Belgium, is known for his involvement in controversial euthanasia deaths including: depressed women, twins who feared becoming blind, a woman with Anorexia Nervosa who was psychologically suffering after being sexually exploited, and Nathan Verhelst who died by euthanasia after a botched sex-change operation. Distelmans is also the President of the Belgium Euthanasia Control and Evaluation Commission.

Gerald Kaufman
The Daily Mail article refers to the tour of Auschwitz as outrageous noted that Jewish leaders and anti-euthanasia leaders are shocked.

Sir Gerald Kaufman a Labour MP in the UK said:
‘To make the notorious Nazi concentration camp of Auschwitz the centre for a congenial study-trip is preposterous, if not obscene.

‘Whatever one’s views on euthanasia – and I am against – it is abominable to describe Auschwitz as an “inspiring venue”. What went on at Auschwitz and the other death-camps was mass murder of innocents – children, women and men.’
Tanni Grey-Thompson
Lord Alex Carlile, a Liberal Democrat member of the House of Lords and the son of Polish Jewish immigrants, said:

‘This is shocking. It will cause offence to a lot of people throughout Europe, whichever side of the argument they are on. I am all in favour of people going to Auschwitz to find out the oppression that happened there, but to describe it as an inspiring setting suggests he is either mad, stupid or incompetent.’
Baroness Tanni Grey-Thompson, the British Paralympian, said: 
‘To describe Auschwitz as “inspiring” is very upsetting and very disturbing. It is appalling.’
Distelmans responded to the Daily Mail reporter by stating:
‘Firstly, this is not a symposium about euthanasia. It’s a study trip focusing on human rights, suffering and palliative care. We will mention euthanasia, but that is not the main goal of the trip. 
Wim Distelmans
‘The participants are all professionals working in palliative care. They work every day with patients who suffer pain and death. 
‘Our main goal is to visit the death camp where all these atrocities took place. 
‘Secondly, many of the participants were not in favour of a law on euthanasia, but changed their mind after the law came into action. 
‘There is obviously no link between euthanasia in Belgium and what happened in Auschwitz. 
‘The Nazis used the term “euthanasia” wrongly.’

UK: Assisted Suicide Bill: "Eligible" Patients May Have Years, Even Decades, to Live.

By Margaret Dore, Esq., MBA
Margaret Dore
www.margaretdore.com or www.choiceillusion.org

In the UK, HL Bill 6 is an assisted suicide law proposed by Lord Falconer, which is based on the Oregon and Washington assisted suicide laws. Bill 6 would legalize assisted suicide for persons with a "terminal illness," defined in terms of a prediction of less than six months to live. [1] The Oregon and Washington laws have a similar six months to live criteria. [2]

Under all three laws, "eligible" patients may have years, even decades, to live. This is true for the following the following reasons:

1. Predictions of life expectancy can be wrong.

Patients may have years or even decades to live because predicting life expectancy is not an exact science. Consider John Norton who was diagnosed with ALS. He was told that he would get progressively worse (be paralyzed) and die in three to five years. Instead, the disease progression stopped on its own. In a 2012 affidavit, at age 74, he states:

If assisted suicide or euthanasia had been available to me in the 1950's, I would have missed the bulk of my life and my life yet to come. (Link) [3]

2. The six months to live is determined without treatment.

Consider Oregon resident, Jeanette Hall, who was diagnosed with cancer and decided to "do" Oregon's law. Her doctor, Kenneth Stevens, didn't believe in assisted suicide and encouraged her to be treated instead. It is now 14 years later and she is "thrilled" to be alive. This is Dr. Steven's affidavit filed by the Canadian government in Leblanc v. Canada, now dismissed, discussing Jeanette. This is Jeanette's affidavit, also filed by the Canadian government in the same case.

3. In Oregon, the six months to live criteria is now being interpreted to include chronic conditions such as diabetes.

Oregon doctor, William Toffler, explains:
Our law applies to “terminal” patients who are predicted to have less than six months to live. In practice, this idea of terminal has recently become stretched to include people with chronic conditions such as chronic lower respiratory disease and diabetes. Persons with these conditions are considered terminal if they are dependent on their medications, such as insulin, to live. They are unlikely to die in less than six months unless they don’t receive their medications. Such persons, with treatment, could otherwise have years or even decades to live. [4]
Margaret Dore is a lawyer in Seattle Washington the President of Choice is an Illusion.

Friday, July 11, 2014

What people mean when they say they want assisted suicide.

By Dr William Toffler (Link), a co-founder of the Physicians for Compassionate Care.

There has been a profound shift in attitude in my state since the voters of Oregon narrowly embraced assisted suicide 11 years ago. A shift that, I believe, has been detrimental to our patients, degraded the quality of medical care, and compromised the integrity of my profession.  

Since assisted suicide has become an option, I have had at least a dozen patients discuss this option with me in my practice. Most of the patients who have broached this issue weren't even terminal. 

One of my first encounters with this kind of request came from a patient with a progressive form of multiple sclerosis. He was in a wheelchair yet lived a very active life. In fact, he was a general contractor and quite productive. While I was seeing him, I asked him about how it affected his life. He acknowledged that multiple sclerosis was a major challenge and told me that if he got too much worse, he might want to “just end it.” “It sounds like you are telling me this because you might ultimately want assistance with your own assisted suicide - if things got a worse,” I said. He nodded affirmatively, and seemed relieved that I seemed to really understand.

I told him that I could readily understand his fear and his frustration and even his belief that assisted suicide might be a good option for him. At the same time, I told him that should he become sicker or weaker, I would work to give him the best care and support available. I told him that no matter how debilitated he might become, that, at least to me, his life was, and would always be, inherently valuable. As such, I would not recommend, nor could I participate in his assisted-suicide. He simply said, "Thank you."


The truth is that we are not islands. How physicians respond to the patient’s request has a profound effect, not only on a patient's choices, but also on their view of themselves and their inherent worth.

When a patient says, "I want to die"; it may simply mean, "I feel useless."

When a patient says, "I don't want to be a burden"; it may really be a question, "Am I a burden?"

When a patient says, "I've lived a long life already"; they may really be saying, "I'm tired. I'm afraid I can't keep going."

And, finally, when a patient says, "I might as well be dead"; they may really be saying, "No one cares about me."

Thursday, July 10, 2014

Assisted Suicide lobby group pushes death by dehydration.

By Wesley Smith - published on his blog on July 9, 2014

Wesley Smith
The people at Compassion and Choices are blatantly mendacious. And the media do not care.

In the wake of the Diane Rehm story, in which she describes her husband committing suicide by self-starvation (“voluntary stop eating and drinking,” or VSED) and pushes legalizing doctor-prescribed death, the suicide-boosting NBC claims that Compassion and Choices wants to prevent these kinds of deaths. From the story:

It’s just the type of death the advocacy group Compassion & Choices, among others, has been fighting to prevent. Instead, John Rehm should have had the option of an assisted death, the group says. They call for “aid in dying” — allowing mentally competent, terminally ill adults to request life-ending medication from a doctor for a peaceful and painless death. It’s legal in several states, but not Maryland….
BULL! Compassion and Choices promotes VSED on its website. It has even published a booklet about suicide by starvation for those who are not terminally ill. From the introduction to Voluntary Stop Eating and Drinking (my emphasis):

Dutch professor now opposes euthanasia. "I was terribly wrong, in fact."

Professor Theo Boer
By Alex Schadenberg
International Chair - Euthanasia Prevention Coalition

The Daily Mail UK is reporting that a former euthanasia supporter, Professor Theo Boer, has told the House of Lords in the UK not to make the same mistake as the Netherlands.


Next week, the British House of Lords will debate the Falconer assisted suicide bill. Lord Falconer is a long-time supporter of assisted suicide who is also known for writing a one-sided report calling for the legalization of assisted death in Britain.

The Daily Mail reported Dr Boer to have told the House of Lords:

‘Don’t do it Britain,’ 
‘Once the genie is out of the bottle, it is not likely ever to go back in again.’
According to the Daily Mail report, Dr Boer, who is an academic in the field of ethics, had argued seven years ago that a ‘good euthanasia law’ would produce relatively low numbers of deaths. But, speaking in a personal capacity he said that 
he now believed that the very existence of a euthanasia law turns assisted suicide from a last resort into a normal procedure.
Dr Boer, who is a Utrecht University academic who since 2005 has been a member of a review committee that monitors euthanasia deaths stated that:
Euthanasia is now becoming so prevalent in the Netherlands, that it is ‘on the way to becoming a default mode of dying for cancer patients’.

Assisted deaths have increased by about 15 per cent every year since 2008 and the number could hit a record 6,000 this year. 
campaigns for doctor-administered death to be made ever easier ‘will not rest’ until a lethal pill is made available to anyone over 70 who wishes to die. 
‘Some slopes truly are slippery,’
Dr Boer said that he was concerned at the extension of killing to new classes of people, including the demented and the depressed, and the establishment of mobile death units of ‘travelling euthanasing doctors’. He admitted that:
he was ‘wrong – terribly wrong, in fact’ to have believed regulated euthanasia would work. 
‘I used to be a supporter of the Dutch law. But now, with 12 years of experience, I take a very different view.
Tanni Grey-Thompson
The Daily Mail article quoted Paralympian, Baroness Tanni Grey-Thompson, said:

‘What Dr Boer says comes as no surprise. 
‘An assisted dying law is playing with fire, especially when there are no safeguards in place. Lord Falconer’s bill just isn’t fit for purpose.’
The article then quoted disability rights leader, Baroness Jane Campbell who stated:
‘As happens in Holland, Lord Falconer’s bill could end up encompassing significant numbers of seriously ill people.’
The 2013 Netherlands euthanasia statistics have not yet been released but the 2012 Netherlands euthanasia report indicated that there were 4188 reported assisted deaths, which did not include the unreported assisted deaths, that according to a Lancet study released in 2012 accounted for 23% of all assisted deaths. Therefore the real number of assisted deaths in 2012 was likely more than 5100 deaths.

The expansion of euthanasia in the Netherlands has been significant. Last year a healthy woman who was going blind died by euthanasia.


In February the Dutch Health Minister, Edith Schippers admitted that in 2013 there were 45 psychiatric assisted deaths in the Netherlands which was up from 14 in 2012.

Recently one of Netherlands most famous euthanasia advocates, psychiatrist Dr Boudewijn Chabot wrote an opinion in the Dutch newspaper NRC Handelsblad that the Netherlands euthanasia law is derailed.


In his article Chabot referred to several psychiatric euthanasia deaths including:
a 54 year-old woman with a personality disorder, eating disorder and a chronic obsessive-compulsive neurosis.

a physically healthy man of 63 who was working for a government institution. He never had a relationship and the only thing he did his whole life was work. This man had been treated for a long time for depression, but the treatment didn’t work out.
Soon after euthanasia was legalized in the Netherlands some people may have thought that euthanasia would not be abused, but after more than eleven years experience with legal assisted death in the Netherlands and Belgium the message from Dr Boer should cause the world to say NO TO EUTHANASIA.

Wednesday, July 9, 2014

Suicide Prevention Organization issues medical board complaint against Nitschke.

The following article was published in today's Herald Sun, by Beyond Blue chairman, the Hon Jeff Kennett AC. The article confirms that a complaint will be made by that organisation to the Australian Medical Board against Dr Philippe Nitschke. Yesterday, the West Australian Branch of the Australian Medical Association confirmed that they will do likewise.


Earlier, The Black Dog Institute, a suicide prevention group, suggested that they may also make a complaint, but this has not been confirmed. In all, that makes five or possibly six complaints to the medical board in  he last two years including one from HOPE Australia.


Life is the greatest gift we’re given

Hon Jeff Kennett
BEYONDBLUE was founded in 2000, after the deaths — suicides — of two young men in the Western District in 1997.

Since, it has worked nationally to reduce the stigma attached to depression and mental illnesses through education, research and, importantly, public advocacy.

Why? Because two-thirds of suicides are conducted by people suffering emotional or clinical depression. So reducing suicides has been a major underlying reason for beyondblue’s work and very existence.

The Australian Statistician recently released the preliminary suicide toll for 2012: 2535. A figure that will probably grow when final investigations into some deaths are completed. Of those 2535 deaths, 1312, more than half, were people under 45 years of age. To get that number into perspective, 49 Australians a week die by their own hand. That is absolutely unacceptable by any measure.

The national road toll in 2012 was 1310, almost half the suicide rate. Is it therefore any wonder beyondblue, Lifeline, Sane, Black Dog, all governments in Australia, plus many other like-minded organisations, are working separately and collaboratively to reduce the rate of suicide.

The reader of this column might therefore understand my and beyondblue’s disappointment, no, anger, on hearing that Dr Philip Nitschke had “supported” a 49-year-old West Australian man, Nigel Brayley, in perfect health, to end his life.

Tuesday, July 8, 2014

A Jewish Perspective on Euthanasia, Assisted Suicide and Palliative Care.

By Alex Schadenberg
Executive Director - Euthanasia Prevention Coalition


A column written by Don Marmur, Rabbi emeritus at Toronto’s Holy Blossom Temple and published in the Toronto Star on July 7, 2014 under the title: Palliative Care preferable to assisted suicide, offers a Jewish perspective on the issues of euthanasia and assisted suicide.

Marmur's comments are based on the Quebec euthanasia bill 52, which he refers to as unique in North America with implications that effect us all.

Marmur begins by explaining his faith tradition by stating:
My faith teaches that life is God’s gift and, therefore, sacred. For humans, to take it away in murder or suicide is criminal and sinful. Despite its claim to compassion, assisted suicide may be of that ilk.
Marmur then recognizes that palliative care may quicken death but that does not contravene ethics. He wrote:
But my faith also teaches that as God’s creatures we’re obligated to lighten the burden of others and do our utmost to relieve them of suffering. Palliative care for the terminally ill is of that ilk.
Marmur then quotes Rabbi Benny Lau, one of Israel’s outstanding religious leaders, who stated:
“Yes to compassion, no to murder.” ... if doctors cannot cure, they should allow terminally ill patients to die, though without actively helping them to do so.
Another prominent Israeli rabbi, David Stav, is then referred to by Marmur"
 “We fear that the family members or medical staff will exert concealed or open pressure on terminally ill patients, who will choose a ‘respectable’ death in order to make things easier for those staying alive.” 
 “Giving physicians the right to prescribe a life-ending prescription changes the image of doctors in their own eyes and in the eyes of society, and could have a far-reaching impact on the role of doctors and the trust in them.”
Marmur then quotes Mordechai Halperin of Jerusalem, a doctor and a rabbi to have stated:
permitting assisted suicide “will eventually lead to ending the lives of people who ‘are not suitable for us.’” In their endeavour to save taxpayers’ money, states may adopt forms of “mercy killing” in the guise of compassion and compliance with the wishes of citizens. The scandal of the Nazi euthanasia program must never be far from our minds.

Nitschke and euphemisms in the euthanasia & assisted suicide debate


This article was written by Paul Russell, the founder of HOPE: preventing euthanasia & assisted suicide and is Vice Chair of the Euthanasia Prevention Coalition International. This article first appeared in his blog on July 8, 2014 and has been republished with permission.

The recent news concerning Dr Philip Nitschke, Exit International and the suicide death of two men who were not terminally ill has forced the Australian public to confront the issue of assisting someone to die.

As Herald Sun columnist Andrew Bolt points out, this is not something new. Nor is the public commentary from Dr Nitschke at the pointed end of the debate: when a bill is before an Australian legislature.

When Nitschke comments on such bills there's a noticeable cringe factor among state-based supporters of such legislation, with the most common response being that Nitschke's comments 'are not helpful'.

Monday, July 7, 2014

New Palliative Care Award named after Jean Echlin

The Jean Echlin Award for Ethics in Palliative care was announced by the deVeber Institute on July 3. In its announcement, the deVeber Institute stated that the new award recognizes and honours the important work done by Jean Echlin in her long and distinguished career in palliative care.

Jean Echlin was the founding Vice President of the Euthanasia Prevention Coalition.

The Windsor Star announced the Jean Echlin award by recognizing as a pioneer in palliative care. The Windsor Star stated:
One of Ontario’s leading pioneers in advances in palliative care was honoured Friday with a major award in the field dedicated in her name. 
Jean Echlin, 82, who continues to teach nursing courses at the University of Windsor and hold roles with several nursing and end-of-life care provincial organizations, will have a new annual award for “ethics in palliative care” in her name under the deVeber Institute for Bioethics & Social Research in Toronto. 
Echlin was instrumental in the founding of the Hospice of Windsor and Essex County’s clinical and volunteer programs. She also served as executive director of the Hospice.